
Endocrine Medications
Hypothyroidism
In primary hypothyroidism, the thyroid does not produce enough hormones (T3, T4). In response to low circulating thyroid hormones, the pituitary continues to release TSH, resulting in high levels of circulating TSH. Levothyroxine is usually started or increased to lead to a euthyroid (normal) state.
Several medications impair the absorption of levothyroxine (Synthroid). Common offenders are antacids, calcium, and iron preparations. Some of these could be present in several over-the-counter multivitamin and mineral tablets. Therefore, clients with hypothyroidism should be instructed to take levothyroxine on an empty stomach, preferably in the morning, separately from other medications.
The expected therapeutic response to levothyroxine (Synthroid) includes an increased sense of well-being with elevated mood, greater energy levels, and a heart rate within normal limits. It takes up to 8 weeks to see the full effect of pharmacological therapy.
Clients receiving thyroid hormone replacement therapy (levothyroxine sodium) should understand that treatment is lifelong and be taught the signs of excess hormone (eg, tachycardia/palpitations, weight loss, insomnia). The medication is best absorbed on an empty stomach and is safe to take during pregnancy.
Hypothyroidism during pregnancy places clients at increased risk for other complications of pregnancy (eg, preeclampsia, placental abruption, preterm labor). Symptoms of hypothyroidism may include fatigue, cold intolerance, constipation, dry skin, and brittle hair/nails. Levothyroxine (Synthroid) is the first-line medication for treatment of hypothyroidism during pregnancy. The client may experience some relief of symptoms beginning approximately 3-4 weeks after initiating levothyroxine therapy
Hyperthyroidism
Radioactive iodine treats hyperthyroidism by damaging or destroying the thyroid gland. After ingesting radioactive iodine, clients and their bodily secretions are radioactive. They should avoid pregnant women and children, use a separate toilet and disposable tableware, sleep in a separate bed, and isolate personal laundry.
Beta-adrenergic blockers (atenolol, metoprolol, and propranolol) are given to relieve some of the symptoms of thyrotoxicosis. They block the effects of the sympathetic nervous system and treat symptoms such as tachycardia, hypertension, irritability, tremors, and nervousness in hyperthyroidism.
Diseases
Addison disease is characterized by adrenal insufficiency and hypofunction of hormones. The nurse caring for a client who is prescribed long-term corticosteroid therapy should instruct the client to report signs of infection and hyperglycemia. Anticipatory guidance should include the need to increase the dose of corticosteroid during times of stress (eg, surgery)
In clients taking corticosteroids, it is imperative to notify the health care provider of signs and symptoms of infection, even a low-grade fever. The anti-inflammatory properties of corticosteroids can mask signs of infection, and their immunosuppressive effects can cause the infection to develop and spread quickly.
Diabetes
Insulin is a medication commonly used to control and lower blood glucose levels in clients with diabetes mellitus. Clients may require a combination of long-acting insulin (eg, glargine) with rapid- (eg, lispro) or short-acting (eg, regular) insulin to manage glucose levels. The different onsets, peaks, and durations mimic the body’s natural insulin levels and enhance glycemic control. Insulin glargine, a long-acting (basal) insulin, has no peak and may last 24 hours or longer. Short-acting insulins peak 2-5 hours after administration and last approximately 5-8 hours.
Subcutaneous injection is the indicated route for NPH insulin administration; it should never be administered IV push. Regular insulin is the only insulin that can be administered IV push.
Metformin is an oral antidiabetic medication used to manage hyperglycemia in clients with type 2 diabetes. Metformin increases the sensitivity of insulin receptors in cells and reduces glucose production by the liver. These actions increase the efficacy of insulin present in the body and prevent large rises in blood glucose after meals
Thiazolidinediones (rosiglitazone [Avandia] and pioglitazone [Actos]) are used to treat type 2 diabetes mellitus. These agents improve insulin sensitivity but do not release excess insulin, leading to a low risk for hypoglycemia (similar to metformin). These drugs can worsen heart failure by causing fluid retention and increase the risk of bladder cancer. Heart failure or volume overload is a contraindication to thiazolidinedione use. These medications also increase the risk of cardiovascular events such as myocardial infarction.
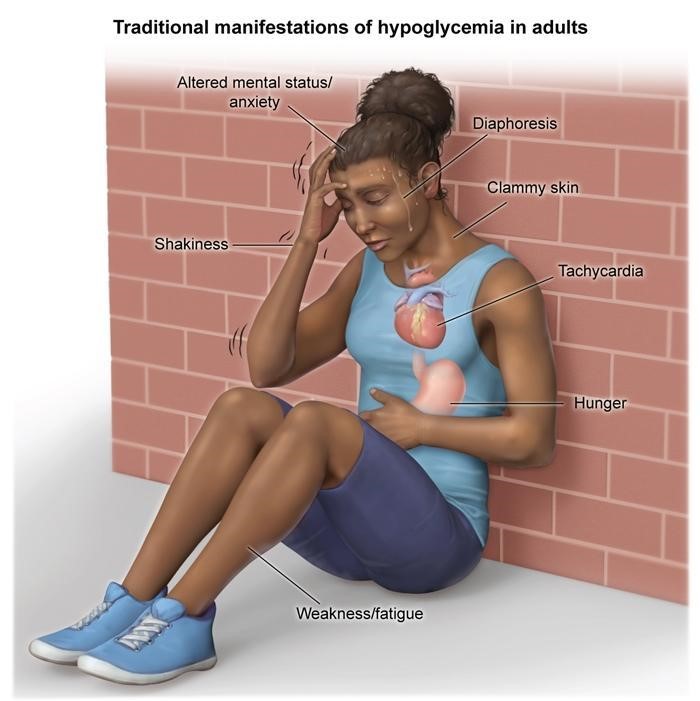
Desmopressin is a medication often used to treat central diabetes insipidus, a disease characterized by reduced antidiuretic hormone (ADH) levels that may result in dehydration and hypernatremia. Desmopressin mimics the effects of naturally occurring ADH, which increases renal water resorption and concentrates urine. However, this effect also increases the risk for water intoxication from decreased urine output.
Clients taking desmopressin for diabetes insipidus are at risk for water intoxication and hyponatremia. Client reports of headache, mental status change, and/or muscle weakness may indicate hyponatremia from water intoxication and should be reported to the health care provider immediately.
An insulin pump is a small, battery-operated device about the size of a pager. The infusion set holds a syringe (reservoir) filled with rapid-acting insulin (175-315 units) and delivers the drug from the pump to the client through a needle or catheter that is usually secured to the abdomen with an adhesive patch. The pump delivers insulin in 2 ways:
- As a steady, measured, and continuous dose (basal rate) 24 hours a day
- As an intermittent dose (bolus) administered manually at mealtime to cover carbohydrate intake and as a supplemental dose to correct pre- or postprandial hyperglycemia.
CSII therapy delivers the insulin more accurately than injections, so the client experiences fewer swings in blood glucose levels and hypoglycemic episodes, as compared with the administration of insulin using a needle and syringe, or pen.
When caring for a hospitalized client wearing an insulin pump, the priority nursing action is to assess the client’s mental capacity to determine the ability to self-manage the pump safely.
NCLEX TIPS
Mixing NPH and Regular Insulin for Injection Mixing two types of insulin for injection such as regular insulin, which is short acting and NPH insulin, which has a moderate peak of action is often indicated for patients who chronically require insulin therapy. To prevent contamination from multi-use vials the nurse must be familiar with the procedure and special considerations when combining two types of insulin in one syringe for injection.
The order and the number of units of NPH insulin and regular insulin should be verified in the medication administration record (MAR). Note that the shorter acting insulin is drawn up first. The proper supplies should also be selected including the vials of the insulin, syringe, alcohol pads, and proper PPE.
Roll the NPH insulin between your hands to evenly distrubute the medication throughout the vial. Upon completion of rolling the NPH insulin, it should appear uniformly cloudy.
Multiuse vials require the use of an alcohol preparation prior to use of the vial for medication administration.
An injection of air equal to the number of units of insulin allows for the medication to be easily withdrawn from the multiuse vial. Vials of medication are vacuum-sealed and failure to inject air into the vial first could create difficulty in attempting to withdraw the medication. Performing this process after injecting air into NPH insulin allows one to immediately withdraw from the regular insulin vial, which must be performed prior to withdrawing the NPH insulin.
Withdraw the number of units of regular insulin (clear) ordered into the syringe. Vials should be inverted to withdraw medications.
Withdraw the number of units of NPH (cloudy) insulin into the syringe being careful to draw the exact number. Vials should be inverted to withdraw medications.
Once the amount of insulin is withdrawn it should be verified with a second nurse. The second nurse should compare the types of insulin, the units, and the mixed syringe with the MAR.
If the incorrect amount of insulin was withdrawn, the entire syringe should be discarded and the process should be started over. Never return additional amounts withdrawn back into the multiuse vial as this may cause mixing of insulin types.